
Venous Leg Ulcers
- Home
- Venous Leg Ulcers
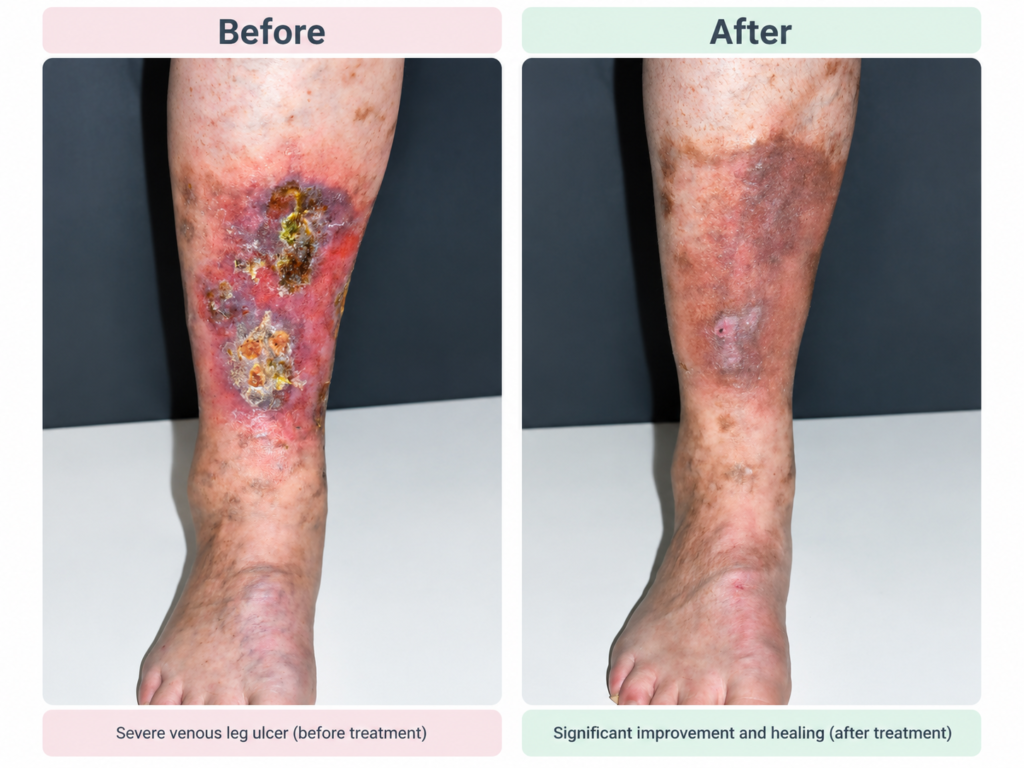
Venous Leg Ulcers in Melbourne: Symptoms, Causes and Treatment
Venous leg ulcers are slow-healing wounds that commonly develop on the lower leg, particularly near the ankle. They are often associated with chronic venous insufficiency, a condition in which the leg veins do not return blood effectively towards the heart.
When pressure remains elevated in the leg veins, fluid and inflammatory changes can affect the surrounding skin and tissues. Over time, the skin may become damaged and an open wound can develop.
Symptoms may include leg swelling, skin discolouration, itching, discomfort and fluid leaking from the wound. However, not every leg ulcer is caused by venous disease. Arterial disease, diabetes, pressure injuries and other medical conditions can also contribute to wounds that do not heal.
A leg ulcer that is not healing requires medical assessment. Identifying the underlying cause is important because treatment differs depending on whether the ulcer is venous, arterial or associated with more than one condition.
Vein Care provides assessment of venous conditions in Melbourne. Where appropriate, clinical examination and vascular investigations may help determine whether underlying venous reflux is contributing to a leg ulcer and whether further treatment or referral is needed.
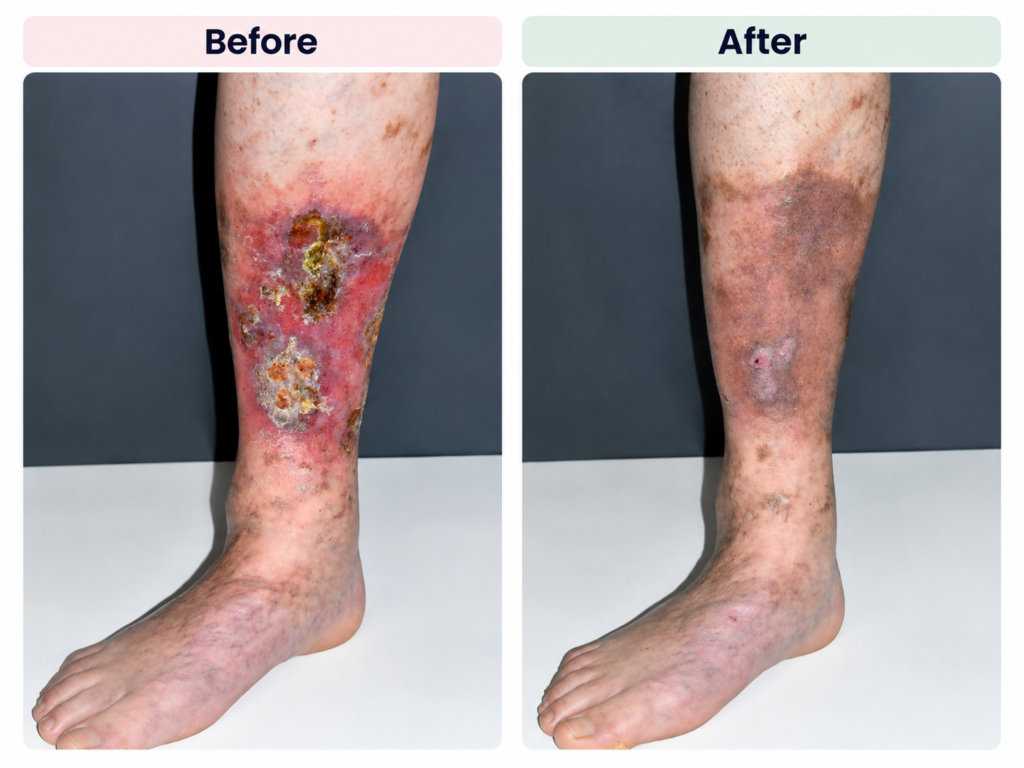
What Are Venous Leg Ulcers?
A venous leg ulcer is an open wound that develops when long-standing problems with blood flow through the leg veins contribute to skin and tissue damage. These ulcers commonly occur on the inner lower leg, near the ankle.
Venous ulcers may be shallow or deeper and can have irregular edges. The surrounding skin may appear swollen, darkened, dry, itchy or thickened, and the wound may release fluid.
Common features include:
A wound on the lower leg that is slow to heal
Swelling around the ankle or lower leg
Brown or reddish skin discolouration
Itching, irritation or eczema-like skin changes
Fluid discharge from the wound
Aching, heaviness or discomfort
Hardened or thickened skin around the lower leg
These features may suggest venous disease, but they do not confirm the cause. A clinician should assess a non-healing wound and determine whether additional investigations are needed.
What Causes Venous Leg Ulcers?
Venous leg ulcers commonly develop as a consequence of chronic venous hypertension, which means persistently increased pressure within the veins of the lower legs.
This may occur when vein valves do not function effectively, allowing blood to flow backwards and collect in the leg veins. Previous deep vein thrombosis may also damage the venous system and contribute to long-term circulation problems.
Factors associated with venous ulcer development include:
Chronic venous insufficiency: Reduced effectiveness of blood return through the leg veins.
Varicose veins and venous reflux: Abnormal backward blood flow can contribute to increased venous pressure.
Previous deep vein thrombosis: A blood clot may lead to lasting vein damage or obstruction.
Increasing age: Changes in venous function and tissue health may increase vulnerability.
Reduced mobility: Limited calf-muscle activity can impair venous return.
Excess body weight: Additional pressure may worsen existing venous problems.
Previous leg injury or ulceration: Tissue damage and previous ulcers may increase the likelihood of future problems.
Not every leg ulcer is venous. Arterial disease, diabetes, pressure injuries and other conditions may produce wounds with different causes and treatment requirements.
A clinical assessment is necessary to identify the likely cause and guide appropriate care.
How Are Venous Leg Ulcers Diagnosed?
Assessment begins with a review of the wound, surrounding skin, symptoms, medical history and factors that may affect healing.
A clinician may examine circulation in the legs and feet, assess swelling and check for signs of infection or other conditions that could contribute to the wound.
Investigations may include:
Ankle-brachial pressure index (ABPI): Compares blood pressure in the ankle and arm to help assess arterial circulation and guide compression treatment decisions.
Duplex ultrasound: May be used to assess venous reflux, previous vein damage or obstruction and, where indicated, arterial blood flow.
Additional investigations: Blood tests, wound sampling, specialist imaging or tissue biopsy may be considered in selected cases.
Assessing arterial circulation is particularly important before applying sustained compression therapy. Some patients require further vascular assessment when the initial tests are inconclusive or unreliable.
Diagnosis and treatment planning should account for the possibility that more than one condition is contributing to the wound.
Learn more about vascular ultrasound and mapping.
How Are Venous Leg Ulcers Treated?
Treatment aims to support wound healing, manage symptoms, address underlying venous problems where appropriate and reduce the likelihood of recurrence.
The recommended approach depends on the ulcer’s cause, severity, arterial circulation, medical history and individual needs.
Compression Therapy
Appropriately selected compression bandages or stockings are a key treatment for many venous leg ulcers. Compression can help reduce swelling and improve venous return.
Compression should be prescribed and fitted following appropriate clinical assessment. It may need to be modified or avoided in patients with significant arterial circulation problems or other contraindications.
Wound Care and Dressings
Suitable dressings help protect the wound and manage fluid discharge. A clinician or wound-care professional may recommend cleansing, dressing changes and removal of non-viable tissue when appropriate.
The dressing choice depends on the wound’s characteristics, surrounding skin and healing progress.
Managing Infection
Not every leg ulcer requires antibiotics. Antibiotic treatment may be recommended when clinical signs indicate infection.
Increasing redness, warmth, pain, swelling, discharge or fever should prompt medical assessment.
Leg Elevation and Movement
Leg elevation, walking and appropriate ankle movements may help support venous circulation and reduce swelling in selected patients.
Activity advice should reflect the patient’s mobility, circulation and overall medical condition.
Assessment and Treatment of Underlying Venous Disease
When underlying superficial venous reflux is identified, endovenous laser treatment (EVLT) may be considered for selected patients, depending on their clinical findings and treatment suitability.
In some cases, ultrasound-guided sclerotherapy (UGS) may be considered to treat suitable refluxing superficial veins. The choice of procedure depends on the venous anatomy, ulcer characteristics and individual clinical circumstances.
Such procedures do not replace appropriate wound care or compression when indicated.
Ongoing Monitoring
Regular review helps assess healing progress, adjust treatment and identify complications. Some patients require coordinated care involving their GP, wound-care team and vascular specialists.
Healing times vary, and recurrence remains possible even after an ulcer has healed.
When Should You Seek Medical Help for a Leg Ulcer?
A leg ulcer that is not healing should be assessed by a healthcare professional, even if it is not particularly painful.
Seek prompt medical assessment if you notice:
Increasing redness, warmth or swelling around the wound
Worsening pain or tenderness
Pus or new unpleasant-smelling discharge
Fever or feeling generally unwell
A wound that becomes larger or deeper
New areas of skin breakdown or darkening
Seek urgent medical care if you develop severe pain, rapidly spreading redness, a cold or unusually pale foot, or sudden changes in sensation or movement.
Call 000 immediately for life-threatening symptoms, such as collapse, severe breathing difficulties or signs of a serious systemic illness.
Do not start high-strength compression bandages or stockings without appropriate clinical advice, particularly if you have symptoms of reduced arterial circulation.
What Is the Difference Between Venous and Arterial Leg Ulcers?
Venous and arterial leg ulcers are both types of open wounds, but they develop through different mechanisms and may require different treatment approaches.
Venous leg ulcers commonly develop when long-standing high pressure in the leg veins contributes to skin and tissue damage. They often occur around the inner ankle and may be accompanied by leg swelling, skin discolouration, eczema-like changes or fluid discharge.
Arterial leg ulcers develop when reduced arterial blood supply limits the oxygen and nutrients reaching the skin and other tissues. They may occur on the feet, toes or lower legs and can be associated with pain, a cool foot or changes in skin colour.
Some patients have both venous and arterial disease, sometimes called mixed-aetiology leg ulcers.
Wound location and appearance can provide clues, but they cannot reliably establish the cause on their own.
Clinical assessment, including appropriate evaluation of arterial circulation and venous function, helps determine the underlying cause and guide safe treatment.
Compression therapy may need to be modified or avoided when significant arterial disease is present.
Venous Leg Ulcer Assessment in Melbourne
Vein Care provides assessment of varicose veins and related venous conditions across Melbourne.
For patients with venous leg ulcers, clinical review and appropriate vascular investigations may help identify whether underlying venous disease is contributing to the wound.
Treatment recommendations depend on individual clinical findings. Patients may also require wound-care services, medical management or referral to another specialist.
For information about other conditions affecting the leg veins, explore our vein conditions overview.
For non-emergency venous concerns, appointments can be arranged at Vein Care's Camberwell, Sydenham and Boronia clinics.
If a wound is becoming rapidly worse or you have signs of serious infection, seek urgent medical care rather than waiting for a routine appointment.
Address : Suite 307, 685 Burke Road Camberwell VIC 3124
Appointments required.
Please confirm current availability when booking.
Address : 574 Melton Highway
Sydenham VIC 3037
Appointments required.
Please confirm current availability when booking.
Address : 157 Scoresby Road
Boronia VIC 3155
Appointments required.
Please call ahead to confirm current availability.
Consultation and treatment availability may vary between clinic locations. Please confirm available services at your preferred location when booking.
Frequently Asked Questions
A venous leg ulcer is an open wound that develops on the lower leg, commonly near the ankle, when long-term problems with blood flow through the veins contribute to skin damage.
Venous leg ulcers are often associated with chronic venous insufficiency and may occur alongside leg swelling, skin discolouration, itching or discomfort. A clinical assessment is necessary to determine the cause of a leg ulcer.
Venous leg ulcers commonly develop because of persistent high pressure within the leg veins, known as chronic venous hypertension.
This may result from damaged vein valves, venous reflux or previous deep vein thrombosis. Over time, increased venous pressure can contribute to inflammation, skin changes and tissue breakdown, particularly around the lower leg and ankle.
Venous ulcers commonly occur around the inner ankle and may be associated with swelling, skin discolouration and fluid discharge. Arterial ulcers may occur on the feet, toes or pressure points and can be associated with reduced blood supply, a cool foot or significant pain.
However, appearance alone cannot reliably determine the cause. Some wounds involve both venous and arterial disease.
Clinical examination, assessment of arterial circulation and appropriate vascular investigations help guide diagnosis and treatment.
Some wounds may improve, but venous leg ulcers often require appropriate wound care and management of underlying venous pressure to support healing.
Without suitable assessment and treatment, ulcers may remain open, become larger, develop complications or recur after healing.
A healthcare professional can assess the wound, identify contributing conditions and recommend appropriate care.
No. Compression therapy is an important treatment for many venous leg ulcers, but it is not suitable for everyone.
Before sustained compression is prescribed, a clinician should assess arterial circulation, commonly using an ankle-brachial pressure index (ABPI) or other appropriate investigations.
Patients with significant arterial disease or other contraindications may require modified compression or a different treatment approach.
Do not apply high-strength compression bandages or stockings without appropriate clinical advice.
Healing time varies depending on the ulcer's size, duration, severity, arterial circulation, underlying venous disease and other medical conditions.
Some venous leg ulcers heal over weeks or months with appropriate treatment, while others require longer-term care.
Compression therapy, wound management, monitoring and treatment of underlying venous problems may support healing when clinically appropriate. No specific healing time can be guaranteed.
Yes. Venous leg ulcers can recur, particularly when underlying venous hypertension or chronic venous insufficiency persists.
Depending on individual circumstances, ongoing compression, appropriate physical activity, skin care and management of underlying venous disease may help reduce recurrence risk.
Regular monitoring is important, especially for patients who have previously experienced a venous leg ulcer.
In selected patients, treating underlying superficial venous reflux may support ulcer healing and help reduce recurrence risk when combined with appropriate wound care and compression.
Procedures such as endovenous laser treatment or ultrasound-guided sclerotherapy may be considered when clinically indicated.
These treatments are not appropriate for every leg ulcer. A clinical assessment, including suitable vascular investigations, helps determine whether an intervention may be beneficial.
Seek prompt medical assessment if a leg ulcer becomes increasingly painful, swollen, red or warm, develops pus or unpleasant-smelling discharge, becomes larger, or is accompanied by fever.
Seek urgent medical care if you develop rapidly spreading redness, severe pain, a cold or unusually pale foot, or sudden loss of sensation or movement.
Call 000 immediately if you experience collapse, severe breathing difficulties or other life-threatening symptoms.
A wound that is not healing also requires medical assessment, even if there are no obvious signs of infection.
